

Six paragraphs, each carrying the weight of a story, a crisis, and a human truth. Here is the summarized and humanized version of that content.
—
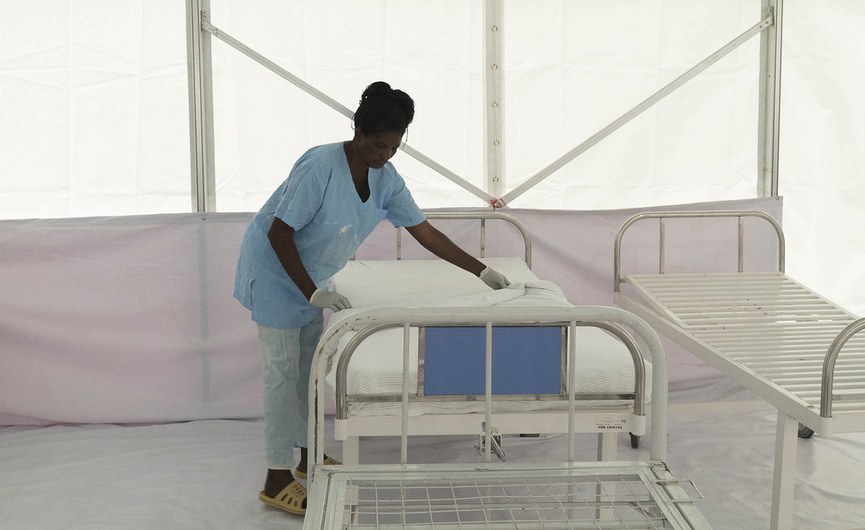
The morning air hung heavy with humidity and suspicion in a small eastern Congolese town, and Amina, a nurse in her early thirties, had seen both before. She pulled on the heavy plastic apron and gloves, the sweat already beading on her forehead, and tried to smile behind her face shield. In the isolation ward, a five-year-old boy with a fever and bloodshot eyes lay curled on a thin mattress, his mother crouched beside him, terrified. Amina’s job was simple: comfort, treat, and contain the Ebola virus. But outside the clinic gates, a more airy and equally lethal enemy was doing its work. A cellphone video had been circulating for hours, a man in a torn shirt claiming that the white-coated responders were not saving people, but infecting them with needles filled with poison. The crowd gathering at the gate was not abusive, not yet—but there was a tightness in their faces, a hand on a machete, a stone being passed between fingers. Amina knew that in this region, an aid worker’s worst moment is not the virus in the syringe; it is the rumor in the air. Misinformation, she thought, spreads like a fire in dry grass, faster than any ambulance, and far more difficult to quarantine. The global narrative often focuses on the science of Ebola and the race to develop vaccines, but behind every containment line is another story, less clinical and deeply human: health workers who shrug on their protective gear not only against a virus but against the suspicion and fear of the very community they came to save. When trust breaks down, the dying become invisible. And a nurse like Amina, who signed up to heal, suddenly becomes a target.
Misinformation takes many shapes, and in the Ebola zones of Africa, it is rarely an accident. It is a deliberate weapon, a survival instinct, a cultural echo, and a social media plague rolled into one. Whispered claims that Ebola is a fabricated disease invented to justify foreign domination have been circulating since the first major outbreaks in West Africa. Across WhatsApp groups, Facebook messenger threads, and voice notes recorded in local languages, rumors mutate faster than the virus itself. Health workers, the story goes, are not delivering medicines but harvesting organs; they are not offering vaccines but setting surveillance chips under the skin; they are paid by the West to turn villages into laboratories of death. In the Democratic Republic of Congo, where Ebola struck repeatedly, some communities came to believe that the chlorine sprayed on doorposts was a poison, that the body bags provided by responders would kill a sick person even before the virus could, and that the red cross on the white vests was a mark of a death squad. These are not simply silly rumors from the uneducated. They are powerful stories born of real pain, of generations of colonial exploitation, of bad experiences with distant authorities, of promises that never arrived. And when such stories find fertile ground, the consequences are violent. There have been burnt health facilities, broken ambulances, and too many workers attacked or killed. The emotional toll is vast: a doctor who survived an attack no longer sees his job as healing but as siege warfare. Every checkpoint on the road to a clinic becomes a test of whether the community will let help through. In one memorable conversation with a field technician, he told me, “I used to worry about wearing out my gloves. Now I worry about wearing out my welcome.” That fear, that uncertainty, is the hidden casualty of misinformation.
The human impact on health workers is not just physical danger; it is an overwhelming moral and psychological exhaustion. Imagine a young doctor who trained for years, who left a comfortable city post to volunteer in a remote area, only to be accused of murdering the very people she has come to assist. That doctor must move through the day with heart racing, listening for the shift in tone outside the clinic walls, not knowing if the neighbor she greeted in the morning is the same man who will throw a rock at her by midnight. She will begin to doubt her own mission. Perhaps she will withdraw into the safety of the compound, stop visiting the villages, stop listening to the elders. And that isolation, in turn, feeds the next generation of rumors. Health workers are being forced to become not only clinicians but also security analysts, psychologists, and diplomats. They must negotiate with angry young men brandishing machetes for permission to vaccinate children. They must explain to grieving families why they cannot touch the body of their beloved mother when every instinct demands a final embrace. The virus thrives on body fluids, so safe burial protocols forbid touching, washing, and kissing the dead—but those protocols, however scientifically sound, feel like an affront to love. When local communities are told to abandon rituals that have honored ancestors for centuries, with no alternative meaning offered, they listen instead to whoever tells them that the foreigners want to erase their culture. Health workers are caught in the crossfire, often paying with their lives or their sanity for the sins of a global system that did not do enough to communicate with empathy before it arrived with tubes and syringes. We build field hospitals in a week, and then wonder why trust, which has been lost for decades, cannot be rebuilt in a day.
Root causes run deep. Part of the reason misinformation clings so stubbornly in places like eastern DRC and the borderlands of Uganda is that outsiders have often arrived with good intentions and a breathtaking lack of understanding. Ebola outbreaks cluster in regions that have experienced war, displacement, and fragile governance. In such places, a foreign health worker wearing a full hazmat suit looks less like a symbol of hope and more like an alien invader. Accusations about Western powers injecting the virus directly recall centuries of mistreatment, from the violent extraction of resources to medical experiments that rarely benefited local people. These are not irrational fears; they are learned survival responses. When the response team shows up in a convoy of white trucks, residents rightly ask: “Where were you when our children died of malaria?” “Why is all this attention on a hemorrhagic fever that affects fewer people than measles?” Social media amplifies those questions into grotesque conspiracy theories. Young men with a smartphone and a grudge can outshout an entire team of epidemiologists. Meanwhile, local leaders, religious figures, and traditional healers, the true gatekeepers of public opinion, have often been left off the invitation list. When a village chief learns about a new vaccine from a TikTok video before he learns it from the government, the damage is already done. Documentation from recent outbreaks shows again and again that health workers were attacked not because their treatment was wrong, but because nobody had built the trust necessary for the community to hear the right message. In places where the state is absent, where every stranger is a potential threat, people cling to the familiar. And the familiar, in times of crisis, is often rumor.
The solution is not simply to fight misinformation with louder counterclaims. You cannot disinfect a fear with a Twitter thread. What works is slower, humbler, and more personal. It involves handing the megaphone to local women, church leaders, bus drivers, market vendors, and survivors who have personally lived through Ebola and emerged to tell the story. In some communities, the most effective vaccine advocates are former Ebola patients themselves, people who can hold up their healthy children and say, “I was in that ward, and they cared for me.” Health workers must be trained to stop, sit down, and listen to the anger before they ever open a medical kit. Instead of saying, “You were misinformed,” they must say, “I understand why you would be suspicious. Let me share what I have seen with my own eyes.” Community engagement teams should be embedded long before the outbreak begins, not parachuted in at the peak of panic. They should support local clinics year-round, drill water wells, train rural health aides, so that when an emergency strikes, the presence of an outsider is no longer a novelty or a threat. The most successful responses to recent Ebolas have been those where response leaders walked into mosques and churches, sat on woven mats, drank tea with leaders, and asked not only for permission but for partnership. They helped shape burial rituals to honor the dead while reducing transmission, using dignified, transparent plastic body bags and allowing families to see the body through a window before the burial. They hired local young men to drive ambulances, to guard facilities, to speak to their peers in words that real people use. One aid doctor described the turning point in his field station: “The moment we stopped calling locals ‘beneficiaries’ and started calling them ‘colleagues,’ the attacks stopped.” That is not a slogan; it is the ground truth.
Ultimately, the story of misinformation and Ebola is a story about humanity in its most fragile, magnificent state. Health workers are not saints, and they are not saviors. They are human beings who forget their own birthdays during an outbreak, who cry in private after losing a child whose mother did not trust them enough to come back the next day, who love the smell of roasted plantains and dread the sound of a phone ringing at night. The communities they serve are not ignorant mobs; they are fathers and mothers protecting their families with the only tools they have—suspicion of the unknown, loyalty to tradition, and a deep, rightful demand for respect. A nurse in a hazmat suit and a mother outside the gate are not enemies. They are both trying to love. The difference is that the nurse has the science, and the mother has the fear. Story by story, visit by visit, conversation by conversation, the gap between them can be closed. But it will never be closed from behind a desk or from inside an armored vehicle. It will be closed when a health worker gently peels off her glove, takes a grandmother’s hand, and says simply, in the local tongue, “I am here for your family, and I will not abandon you.” Misinformation will always be with us; it is a watermark of human anxiety. But compassion, when practiced patiently and on the ground, is a stubborn element. It endures. It outlasts the virus, outwits the rumor, and gives a young nurse like Amina the courage, every single morning, to step back through the gates of a dangerous place and offer care to the very people who once doubted her. That is the real victory, not a vaccine count but a reconciliation. And in the long, weary fight against Ebola, that reconciliation—not equipment, not funding—is the most powerful antidote we have.