

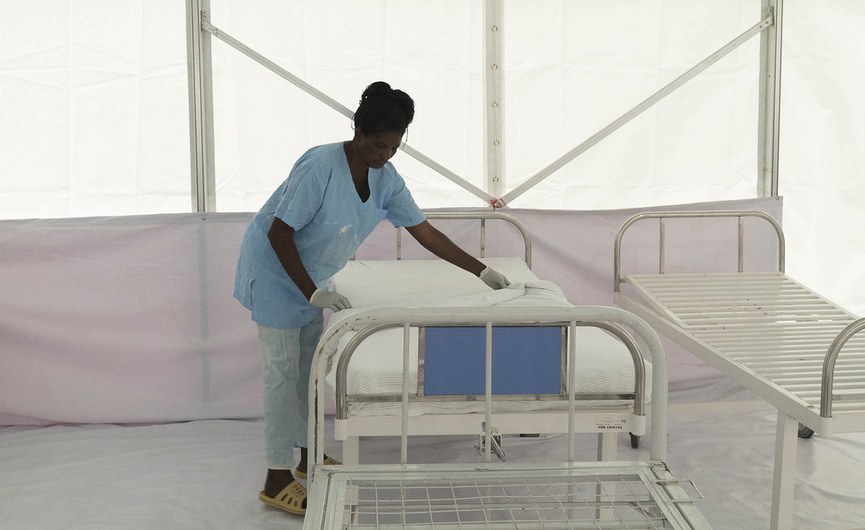
GENEVA — On a late October morning, grief and anger rippled through the global nursing community. In the Democratic Republic of Congo, a nurse had gone to respond to an Ebola case—an act of courage that should have been met with gratitude, not violence. Instead, according to reports, young men armed with machetes killed the nurse, leaving colleagues and communities in shock. The news reached Geneva, where Howard Catton, chief executive of the International Council of Nurses (ICN), was already familiar with the dangers health workers face. But this attack felt different in a crucial way: it was not the random cruelty of conflict; it was the lethal consequence of misinformation and lost trust. Catton took to social media on Oct. 29 to deliver a stark warning: health misinformation and the breakdown of trust in science are now deadly risks for nurses and health workers. He was not speaking abstractly. The Ebola response in DR Congo had long been hampered by rumors, suspicion, and resistance. For local populations, decades of neglect and failed promises make outsiders easy to doubt—and aid workers in protective gear can look frightening, especially when false stories claim the virus is a hoax or that health teams are stealing blood. In that poisoned atmosphere, a nurse becomes not a lifesaver but a target. The United Nations’ Ebola coordinator and the head of the World Health Organization also deplored the killing, underscoring how seriously the international community viewed the incident. Yet Catton’s message went beyond condemning the murder. He wanted the world to understand the everyday reality of nurses in places like eastern Congo: they walk into uncertainty, often with no protection other than their vocational commitment. When communities have been fed dangerous falsehoods, the same people who need care can become the ones holding machetes. That nurse’s death was not just a tragedy; it was a signal of how fragile healthcare has become in an era of viral rumors and political manipulation. It is a story of one life cut short, but it echoes across every country where health workers are expected to serve faithfully while being accused, threatened, and abandoned by the very systems meant to support them.
Catton’s warning was not simply about the danger of physical attack. It was about the erosion of the social contract between health workers and the people they serve. When a community begins to believe that doctors and nurses have hidden agendas, then vaccines, treatments, and outbreak response teams become fuel for suspicion. The nurse killed in the DR Congo was not the first health worker to be targeted during an Ebola outbreak, and she will not be the last unless something fundamental changes. In moments of crisis, misinformation travels faster than the virus itself. It spreads through social media, through whispered conversations in markets, through leaders who profit from chaos. By the time a nurse arrives to help, there may already be a crowd convinced that she is an enemy. This breakdown in trust is not only a problem in Africa. Catton’s choice to speak out was meant to shake the world out of its complacency. In wealthy countries, too, nurses have faced hostility from patients influenced by conspiracy theories, especially during the COVID-19 pandemic. But in places where health systems are already fragile and there is little protection for front-line workers, the consequences are much more severe. The ICN has been documenting attacks on healthcare workers for years, and the patterns are clear: those who are least protected are most likely to be blamed when a disease appears. The nurse in the DR Congo had volunteered for dangerous work. She trusted that the international community and her own community would support her. Instead, she met machetes. Her death is a measure of how cheaply human decency can be traded for fear.
This warning came in an interview with AllAfrica, and it carried a broader message about how African nations are struggling to build healthcare systems that can meet the needs of their people. One of the trends Catton highlighted was the growing reliance on community health workers. These are not nurses in the traditional sense; they are trained laypeople who provide basic care and health education in local villages. They are often the only help available in remote areas, and they can be enormously valuable. But there is a temptation, Catton argued, to see them as a cheap substitute for professional nurses. Governments and donors may imagine that a low-paid community volunteer can do the job of a registered nurse, but that is both unfair to community workers and dangerous for patients. The reality in many parts of Africa is deeply contradictory. At the same time that registered nurses are leaving the continent by the thousands for high-income countries in Europe and North America, other trained nurses are sitting at home without jobs. Catton described this as both a push and a pull: overseas health systems offer better pay and safer working conditions, so some of Africa’s best-trained professionals leave; meanwhile, the local labor market cannot absorb all the nurses who graduate every year. The result is a kind of double loss. Communities lose the services of nurses who have chosen to stay but cannot find work, and they also lose the nurses who take their expertise abroad. The leadership in African countries, as Catton observed, is increasingly frustrated. During his travels last year, several leaders told him that their countries are being systematically disadvantaged. They train health workers with limited public resources, often using foreign aid or loans, and then those same workers migrate to rich countries that have not paid a cent for their education. It is hard to improve a hospital when your best staff keep leaving, and it is harder still to provide care for the millions who remain. Community health workers can fill some gaps, but they cannot replace the years of training and experience that registered nurses bring to the bedside. Catton’s point was simple: if international partners genuinely want to strengthen health systems in Africa, they need to invest in nurses—not look for cheaper alternatives.
The scale of the crisis is staggering, and it can be measured in numbers that are impossible to ignore. According to UN figures cited by Catton, Africa’s health workforce grew to 5.72 million in 2024, up from 4.3 million in 2018. That sounds like impressive progress, and in some ways it is. More nurses and doctors are being trained than ever before. But the demand is growing even faster. Catton pointed out that the African region currently has only 46 percent of the health workers it needs. In other words, more than half the essential health positions remain unfilled. People are dying not because the science is unknown, but because there is simply not enough skilled staff on the ground to deliver care. The World Health Organization’s Africa 2026 report adds another disturbing layer: an estimated 943,000 trained health workers across the region were unemployed in 2024. That number is particularly cruel. It means there are qualified nurses ready to work, but they cannot find positions. Health ministries may be short on budgets, or jobs are concentrated in urban hospitals while rural areas remain empty. In some countries, bureaucratic obstacles and hiring freezes stand in the way. Whatever the cause, the result is the same: thousands of trained Africans are idle while millions of their neighbors struggle to reach a doctor. Dr Mohamed Yakub Janabi, the WHO regional director for Africa, stated the dilemma plainly. “We are training more health workers than ever before, yet too many remain unemployed while millions go without care,” he said. Speaking in Ghana in May, he warned that without bold investment and coordinated reform to plan, train and retain health workers, universal health coverage will remain out of reach. His words echo what nurses themselves have been saying for years. Training someone to be a nurse is not enough. They need jobs, equipment, supplies, protection and respect. Otherwise, the system collapses under the weight of its own contradictions. A new nurse may graduate with dreams of saving lives, find no job, and then either leave the profession or leave the continent. The money invested in her education disappears with her. The system is not just losing staff; it is losing public resources and, ultimately, losing hope.
When Catton visited African countries last year, he heard a word that shaped many conversations: neo-colonialism. It is a strong term, and those who use it are often dismissed as conspiratorial. But the meaning is not hard to understand. African nations invest scarce public money in educating health professionals, building nursing colleges, and training the next generation of caregivers. Then, after years of effort, a nurse moves to London or Toronto or Paris, where she is welcomed by a wealthy health system facing its own staffing crisis. The receiving country did not pay for her education, did not support her family while she trained, and did not absorb the cost of the many students who never reach the bedside. Yet it benefits from all that preparation. The sending country, meanwhile, loses a nurse it desperately needs and receives nothing in return. Catton, conveying the sentiment, said leaders feel like valuable resources are being taken without adequate compensation. That is the core of the neo-colonial complaint: not simply that people migrate, but that the structure of global healthcare is organized to strip poorer countries of their professionals while richer countries reap the benefits. This is not accidental. Recruitment agencies actively seek out nurses from Africa to fill shortages in high-income countries. Some agencies claim ethical standards, but the flow continues. During the COVID-19 pandemic, the dependence on overseas nurses became even more visible, and the world did not collectively ask how to protect and pay them fairly. Catton’s warning was aimed at this global arrangement. It is a reminder that when a nurse leaves her home country, the people she leaves behind are not just missing a colleague; they are missing the ability to trust that someone will be there when they are sick. The transfer of human talent from poorer to richer countries is a quiet kind of extraction, and it has been happening for so long that many people no longer notice. It is also an insult to the memory of nurses who die on the job, because it suggests that their lives and labor are simply resources to be moved around rather than human beings to be valued.
The numbers that define this crisis reach far beyond Africa. The WHO estimates that the world will face a shortage of at least ten million healthcare workers by 2030, and some organizations project an even larger gap. Pooja Kumar, a global leader at the McKinsey Health Institute, pointed out that this shortage is not evenly distributed. Africa has about seventeen percent of the world’s population, yet it accounts for fifty-two percent of the global shortage. That single statistic shows how unequal healthcare has become. It is absurd: the continent with the heaviest disease burden, the youngest population, and the fastest-growing health needs is the one with the greatest shortage of caregivers. It is also the continent where healthcare workers are most likely to be attacked, abandoned, or misunderstood. The story of the murdered nurse in DR Congo is one extreme expression of this wider breakdown. But it is not only about violence. It is about the nurse who graduates with honors and cannot find a job. It is about the community health worker who is asked to do the work of a registered nurse for a fraction of the pay. It is about the African leader trying to build a clinic while his best staff are recruited away. It is about the global health system that sees these inequalities, acknowledges them in reports, and then continues to fund short-term projects rather than the long-term strengthening of local workforces. Catton’s call is a call for recognition. Nurses are not commodities. They are not cheap substitutes for one another. They are skilled professionals who deserve to work in places where they are safe, valued, and fairly paid. And the people they care for deserve more than promises. To change this, countries need to invest in nursing education, create vacancies for new graduates, provide safe working conditions, and offer decent wages. Wealthy countries that recruit nurses from developing nations need to compensate those nations fairly or, better, stop recruiting from countries that are themselves in crisis. It is not enough to applaud nurses. The public must also understand the damage done when false information turns a helper into an enemy. Misinformation does not just confuse; it kills. The future of global health depends on rebuilding trust in science and in the people who deliver it. That begins with remembering the nurse who went out to fight Ebola and never came home. Her sacrifice should not be wasted on a headline. It should be a catalyst for real change, so that no more nurses have to die in a world that has the knowledge, the resources, and the power to protect them.