

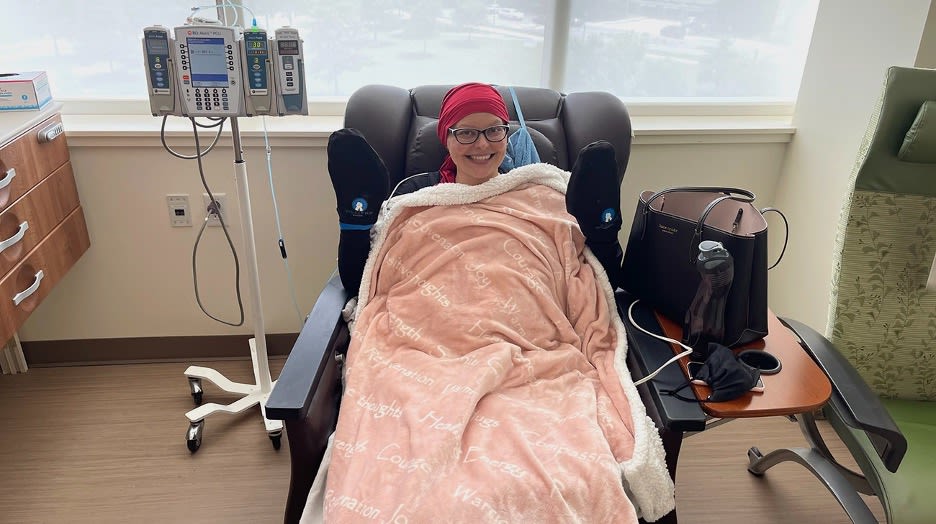
Chase Johnson still remembers the exact moment fear took over. It wasn’t when she found the lump, though that was terrifying enough. It wasn’t even when doctors told her, at just 31 years old, that she had stage 2B triple-negative breast cancer, a rare and aggressive form of the disease. It was after she had done everything right—endured chemotherapy, radiation, and surgery, and been told in 2022 that she was cancer free. Her oncologist delivered the good news with a shadow attached: there was still a 40 percent chance the cancer would come back. For Johnson, a resident of Cary, North Carolina, that number became a constant companion. She had no family history of breast cancer, and she was nearly a decade too young for routine mammograms. The only reason she had been screened at all was her dog, Cato, who kept poking her chest with his nose until she checked and discovered a lump. Now, even after successful treatment, anxiety lingered in her bones, surfacing at every ache, every follow-up appointment, every quiet moment alone. She wanted more than survival—she wanted to feel safe. That search for safety led her to a clinical trial at the Cleveland Clinic testing a new breast cancer vaccine, a shot designed to teach her immune system to recognize and attack any remaining cancer cells before they could take root again. The early results were striking: nearly three-quarters of participants, including Johnson, developed an immune response. “It’s just so promising and as a patient, it gave me a lot of hope,” said Johnson, now 37. “I feel much more protected having done it.”
Johnson’s story sits at the edge of a medical turning point. For the past two decades, researchers have been quietly building toward a new generation of cancer vaccines, and now that future feels close enough to touch. The most exciting work involves mRNA technology, the same platform that produced the COVID-19 vaccines in record time. Instead of preventing an infection, these cancer vaccines are designed to treat the disease after it appears. They work by carrying synthetic genetic instructions—messenger RNA—into the body, teaching a person’s immune system to identify proteins that are unique to their cancer cells. Once the immune system recognizes those markers, it can hunt down and destroy malignant cells wherever they hide. Last month, the pharmaceutical companies Moderna and Merck announced a major milestone: a personalized mRNA cancer vaccine, when combined with an immunotherapy drug, succeeded in a late-stage trial for skin cancer. The news sent waves of hope through the cancer community. For patients like Johnson, who had already experienced the brutal physical and emotional toll of the disease, these vaccines offer the promise of something almost unimaginable: protection against recurrence, a shield that travels inside your own bloodstream. But even as researchers celebrate the breakthroughs, many doctors and scientists are bracing for a dangerous obstacle. They worry that years of vaccine misinformation—amplified by powerful political voices and spread relentlessly on social media—could undermine public trust in these lifesaving tools before they ever become widely available. In particular, they point to a false claim that originated with mRNA COVID vaccines: that these shots can weaken the immune system and “supercharge” tumors, creating a phenomenon falsely called “turbo cancer.” There is no evidence to support this. But the lie has spread so widely that some cancer researchers now fear it will follow them into the clinic.
The cautionary tale that keeps many doctors up at night is the human papillomavirus, or HPV, vaccine. HPV is an extremely common sexually transmitted infection, and certain strains of it can cause cancer—of the cervix, vagina, vulva, penis, anus, mouth, throat, head, and neck. The HPV vaccine was approved by the U.S. Food and Drug Administration in 2006 for girls and women, and expanded to include boys and young men in 2009. It is safe, it is remarkably effective, and when given before a person becomes sexually active, it can prevent nearly all cervical cancers and many other HPV-related cancers. It is, by any measure, one of the greatest public health achievements of the past two decades. Yet in the years since its approval, uptake has stalled, and vaccines that could prevent thousands of deaths each year remain underused. The reasons are complex but familiar: political resistance, cultural discomfort with vaccinating adolescents against a sexually transmitted infection, and a relentless tide of misinformation. Some state and federal lawmakers have themselves spread falsehoods about the vaccine, and the damage has been measurable. For four consecutive years, HPV vaccination rates among teenagers have not budged, and across states, the numbers vary wildly. Dannell Boatman, an assistant professor at the West Virginia University Cancer Institute, co-authored a 2024 study funded by Merck that examined HPV misinformation on social media. What she found was disturbing: while the platforms themselves posted inaccurate content, the most pervasive distortions appeared in user comments, where conspiracy theories flourished. “There were some really wild conspiracy theories about girls in India being killed with the HPV vaccine,” Boatman said. “We also were able to identify a lot of mistrust of authority.” She expects the same dynamics to target new breast cancer vaccines, especially since some people are already spreading false claims that mammograms themselves cause cancer. Still, Boatman is hopeful that a strategy called “inoculation theory” can help. The idea is simple: warn people in advance that they are going to encounter misinformation, refute it, and provide a small piece of evidence explaining why it is false. Forewarned, they are less likely to be swayed.
The political climate has made that work harder. Before he was confirmed as U.S. Secretary of Health and Human Services, Robert F. Kennedy Jr. filed complaints and lawsuits against Merck, the maker of the HPV vaccine, and claimed on social media that the vaccine appeared to increase the risk of cervical cancer, just as he falsely claimed COVID vaccines increased the risk of contracting COVID. Early in his tenure, Kennedy dismissed all 17 members of the HHS vaccine advisory panel, replacing some with vaccine skeptics. Under his leadership, HHS also changed the recommended childhood vaccine schedule for certain diseases, including HPV, though those changes have so far been blocked in federal court. Last month, President Donald Trump signed an executive order separating the measles, mumps, and rubella vaccine into three separate shots and suggested, falsely, that each individual vaccine could fill a “bottle of soda.” The administration has also proposed cutting funding for vaccine research and for studies on vaccine hesitancy—the very research needed to understand and counteract resistance. Michael Osterholm, an epidemiologist and director of the Center for Infectious Disease Research and Policy at the University of Minnesota, watched these developments with alarm. Kennedy’s appointment, he said, actually spurred the creation of the Vaccine Integrity Project, a partnership between his center and the American Medical Association aimed at bolstering public trust in vaccines. The project has published evidence reviews defending some of the vaccines the Trump administration has criticized. Osterholm described the confusion facing ordinary parents who simply want to protect their children, but are bombarded with contradictory messages from the highest levels of government. “They hear from the leaders in public health in their government talk about these vaccines killing people,” he said. “The credibility of 80 years of public health work of vaccines in this country is threatened because of confusion.” In May, the center published a review showing that HPV vaccines are not associated with serious side effects and reduce the risk of cervical cancer by 80 percent in minors vaccinated by age 16, and by 66 percent in people vaccinated after 16. The science is clear. The public conversation is not.
The divide is visible on the ground, in the laws being passed by state legislatures. Nationwide, 78 percent of U.S. teenagers ages 13 to 17 had received at least one dose of the HPV vaccine, but only 63 percent had completed the full series. In some conservative-leaning states, the numbers are strikingly lower: Mississippi’s completion rate is just 31 percent, followed by Oklahoma at 46 percent, Kentucky at 50 percent, Arkansas at 52 percent, and South Carolina at 55 percent. At the other end, Rhode Island, Hawaii, and Massachusetts have rates above 80 percent. Some states, including Alabama and Oregon, have made recent efforts to increase HPV vaccination. But other states are moving in the opposite direction. In May, Iowa’s Republican Governor Kim Reynolds signed a law prohibiting people under 18 from consenting to vaccinations related to sexually transmitted diseases and infections, including HPV. The political resistance often stems from the association between HPV and sexual activity, even though the vaccine simply prevents cancer. Meanwhile, the broader anti-vaccine sentiment is rising in many statehouses. Idaho Democratic State Rep. Brooke Green, a breast cancer survivor herself, said she has watched the distrust increase among her constituents and her legislative colleagues. Green was diagnosed with breast cancer in 2024, just a week before her mother received the same diagnosis. She sees new cancer vaccines as a lifeline, but she is realistic about the uphill battle for acceptance. This year, Idaho Republicans introduced a bill that would have established a two-year moratorium on mRNA immunizations for children and pregnant women. Similar bills appeared in at least a dozen other states, though none were enacted. According to a recent analysis by The New York Times, lawmakers in 34 states introduced 209 bills this year seeking to loosen vaccination rules, limit access to certain vaccines, or cast doubt on their safety. “We are seeing several attempts to address some of the scientific tools that are used to create vaccines, mRNA vaccines and so forth,” Green said. “As a cancer patient, these are life-saving tools that are helping us. I’m thrilled to see these new innovative advancements in medicine for these vaccines. Now, is it going to be widely accepted?” She paused, then answered her own question. “There will be some hesitation and some pushback. But look at the flip side: ‘Do you want breast cancer or do you not? Do you want skin cancer? Do you not?’”
For Chase Johnson, the answer is obvious. This summer, she celebrated five years in remission. Her anxiety, while not completely gone, has settled into something quieter. “I think I’ll always have some sort of low-grade anxiety about it,” she said. “But it’s definitely at a much lower level than it was before vaccination. It’s given me a great, great amount of peace of mind.” Her story is both a triumph of science and a reminder of what is at stake in the fight for trust. Cancer vaccines are not a distant fantasy. They are here, in clinical trials, in early successes, in the bodies of patients like Johnson who are already feeling their protective effect. But they will only fulfill their promise if people are willing to take them. The same misinformation that delayed the HPV vaccine and cast doubt on COVID shots now threatens to cast its shadow over the next generation of cancer treatments. The stakes could not be higher. Every delay, every false claim, every political battle over a vaccine’s safety costs time—and time is the one thing cancer patients do not have. The scientists are ready. The trials are progressing. The question is whether the public will listen, or whether fear will once again prove to be the hardest disease to cure. Johnson knows which side she stands on. She thinks about her dog Cato, who nudged her toward the lump that saved her life. She thinks about the vaccine that gave her peace of mind. And she hopes that other patients, newly diagnosed and scared, will have the same chance she did. “I feel much more protected,” she said. That feeling—that quiet, hard-won sense of safety—is the real promise of the new cancer vaccines. It is worth fighting for.