

Imagine scrolling through social media and seeing a post that claims Papua New Guinea has become a testing ground for a vaccine that African countries have supposedly already rejected. The post warns that the vaccine is part of a depopulation plan, that there are no proper labs in PNG to test it, and that it is aimed at removing Black people. If you are a parent, especially a parent with a young daughter, that kind of language hits hard. It mixes real concerns about medical ethics, colonial history, and the safety of children into one terrifying package. It sounds the way conspiracy theories often do: confident, alarming, and framed as a warning that “they” don’t want you to know. But the emotional power of a claim is not the same as evidence. When fact-checkers investigated the post, they reached a clear verdict: it is false. The HPV vaccine being used in PNG is not a new or experimental product. It has been around and used safely for years. And the claim that all African countries are getting rid of it is not just wrong; it is the exact opposite of what is actually happening across the African continent. Understanding the difference between a scary post and the truth is important because cervical cancer is real, it kills thousands of women every year, and the vaccine is one of the best tools we have to stop it.
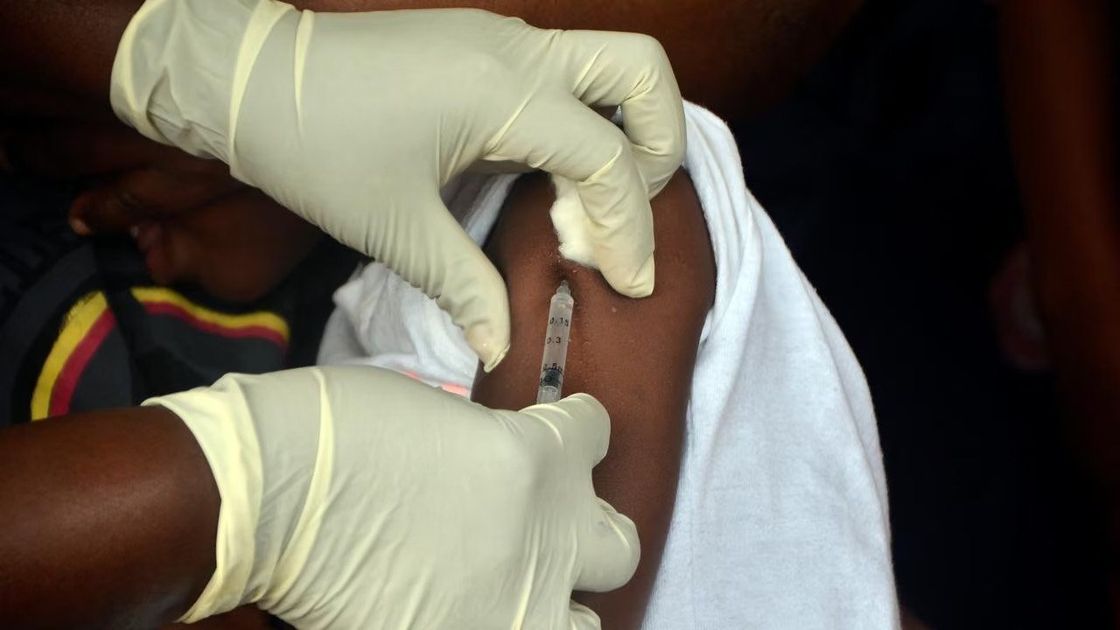
The truth starts with what Papua New Guinea actually did. In September, the PNG government announced a national immunisation program to tackle cervical cancer, and the rollout is being led by the National Department of Health with support from the Australian government, UNICEF, the World Health Organization, Gavi, and community groups. The program aims to vaccinate around 60,000 eligible girls between the ages of nine and fourteen. The vaccine being used is called Gardasil, and it was developed by the pharmaceutical company Merck, with important contributions from Australian researchers. Gardasil is not a mysterious new drug that was just invented for this occasion. It was first approved for use in Australia back in 2006, which means medical professionals around the world have been using it for roughly twenty years. A spokesperson for Gavi, the international organisation that supports immunisation programs in low-income countries, explained that Gardasil has been approved by multiple regulatory authorities and prequalified by the World Health Organization, and that it has been used in immunisation programs around the world for many years. In other words, this is not a vaccine being tested on anyone. It is a vaccine with a long track record. The idea that PNG girls are being used as guinea pigs also ignores the history of HPV vaccination in the Pacific region. According to a spokesperson for UNICEF, HPV vaccines have been used in the Pacific since 2008, including in Fiji and the Solomon Islands. And in Papua New Guinea itself, health authorities in the Western Highlands Province started a local immunisation program in 2024, and almost 29,000 girls in that region have already been vaccinated. So the new national program is not a risky experiment; it is an expansion of work that has already been happening safely in the country and across the region.
Now, let’s talk about what the HPV vaccine actually does and why it matters. HPV stands for human papillomavirus, a very common group of viruses that can be passed from person to person through skin-to-skin contact, including sexual contact. Most of the time, the body clears the virus without any problem, but certain types of HPV can cause abnormal cells to grow and eventually lead to cancer. Cervical cancer is the most well-known of these, but HPV can also cause cancers of the vagina, vulva, anus, penis, and the back of the throat. The HPV vaccine is designed to protect against the types of the virus that are most likely to cause these cancers. It is most effective when given to young people before they are exposed to the virus, which is why health authorities around the world recommend vaccinating girls and boys in their preteen years. The vaccine does not contain live virus, it cannot cause HPV infection, and it has been studied extensively. The claim that “there are no proper labs here in PNG to test them” mixes up the idea of testing a brand-new vaccine in a laboratory with the routine quality checks and safety monitoring that happen during any national vaccination program. Gardasil did not need to be tested in PNG because it had already been through years of clinical trials and approvals before it ever reached the country. What matters now is that the vaccine is delivered safely, stored correctly, and administered by trained health workers, which is exactly what the PNG program, with the support of WHO, UNICEF, and Gavi, is designed to do. The vaccine is not a depopulation tool. It is a cancer prevention tool, and it has been saving lives for nearly twenty years.
The claim about African countries is perhaps the easiest part to fact-check, because the evidence points in the opposite direction. The false social media post said that “all African countries are doing away with this vaccine” and that PNG is being used as a drug testing zone because African nations have supposedly stopped participating. That is not true. In fact, the number of African countries using the HPV vaccine has grown dramatically. Dr Nosheen Safdar, from the WHO’s Regional Office for Africa, was very clear about this. She said the claim that African countries are abandoning HPV vaccination is false. She explained that thirty-six countries in the WHO African Region now vaccinate girls against HPV, which is three times as many as in 2019, and more countries are preparing to join them. She also pointed out that women in Africa face some of the highest cervical cancer death rates in the world, and that the HPV vaccine, which has been used safely around the world for twenty years, is one of the most effective tools available to prevent it. A WHO spokesperson added that no countries in the African region had announced plans to withdraw or stop using the vaccine. So the story is not about African countries turning away from the vaccine. It is about African countries stepping up their vaccination programs because they know cervical cancer is a killer and they know the vaccine works. There is also no evidence that any African country has discontinued the vaccine. The exact opposite is happening: more countries are introducing it, not fewer.
There is one small piece of context that might explain part of the confusion, because not every country in Africa falls into the same WHO region. The WHO African Region covers forty-seven of the fifty-four countries on the African continent. The other seven countries are Djibouti, Egypt, Libya, Morocco, Somalia, Sudan, and Tunisia, and those countries fall under the WHO’s Eastern Mediterranean Region. Of those seven, four include the HPV vaccine in their national immunisation programs, with Somalia, Sudan, and Egypt being the exceptions. The broader point is that even using a stricter, region-by-region view, the claim that “all African countries are doing away with the vaccine” falls apart. The WHO publishes a global map showing which countries include the HPV vaccine in their national immunisation schedules, and that map shows thirty-six of the forty-seven countries in the WHO African region have introduced it. What is more, several of those introductions have happened very recently. Angola, Benin, Comoros, Ghana, Madagascar, Namibia, and Burundi all introduced the HPV vaccine into their national programs, according to the fact-check, in a short period since January 2025. That is the opposite of a continent pulling away from the vaccine. It is a continent that is expanding access to a life-saving tool. The original social media claim also implied that African nations had somehow discovered the vaccine was dangerous and had refused to use it, when in reality the evidence shows just how much African health leaders value it. They have looked at the same clinical data, the same global safety record, and the same devastating burden of cervical cancer, and they have made a choice to protect their daughters and their future generations.
None of this means that people should not ask questions about vaccines. It is completely reasonable for a parent to want to know what is in a vaccine, how it was tested, what side effects it can cause, and why health authorities are recommending it for their child. There is a long and painful history of medical experiments being performed on vulnerable populations without consent, and communities in many parts of the world have every right to be suspicious of outsiders who arrive with needles and promises. Pretending that mistrust does not exist, or telling people to simply “trust the science” without answering their questions, is not helpful. What is helpful is looking at the actual evidence, and the evidence here is very reassuring. The HPV vaccine given to girls in Papua New Guinea is not an untested vaccine. It is not a new vaccine. It is not a vaccine that African countries have rejected. It is a vaccine that has been approved, prequalified, monitored, and used in national programs for around two decades, and it has been embraced by countries across the Pacific, Africa, Europe, the Americas, and Asia. When misinformation spreads online, it often does so because the story it tells is simple, frightening, and easy to share. But reality is more complicated, and in this case reality is also much more hopeful. Cervical cancer is one of the few cancers that we can actually prevent in large numbers, and it is especially important to protect girls in places where screening and treatment services are limited. The rollout in Papua New Guinea is not a test and it is not a trick. It is an effort to save the lives of thousands of women who would otherwise face a preventable cancer. So if you see a post that says otherwise, take a breath, check the source, and remember the facts: the vaccine is safe, it has been used for years, African countries are expanding it, and Papua New Guinea’s girls are being offered protection, not being sacrificed.