

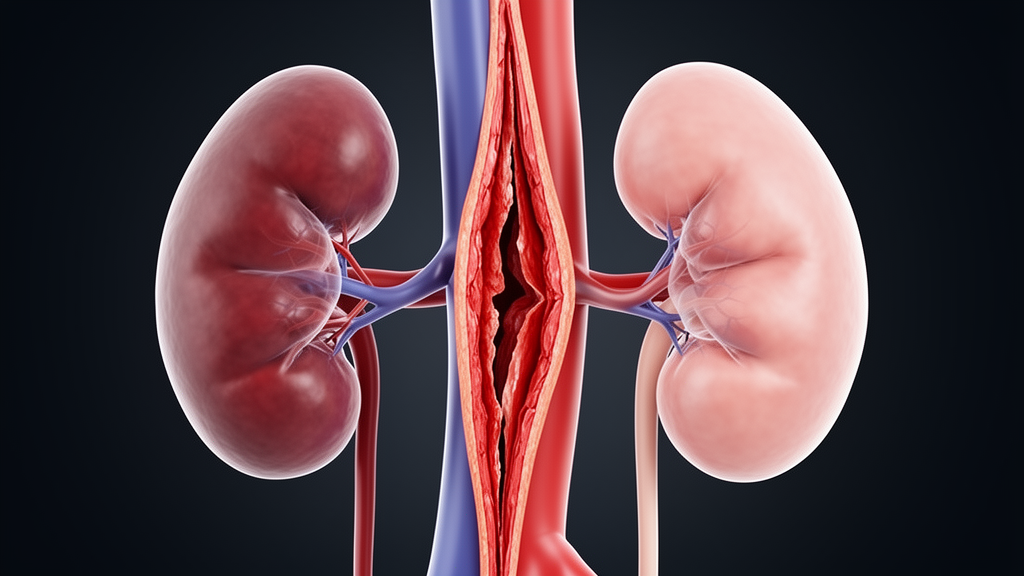
The human body has a remarkable capacity to heal, but sometimes it recovers in ways that puzzle even experienced surgeons. One such mystery involves the kidneys after surgery for aortic dissection—a life-threatening condition in which the inner lining of the aorta, the body’s largest artery, tears and allows blood to flow within the vessel wall, creating a second channel called a false lumen. Even when the repair operation is successful and follow-up imaging shows that the renal artery, the main blood vessel supplying a kidney, looks perfectly open and unobstructed, that kidney may still gradually shrink and lose function over time. This silent atrophy has long frustrated clinicians because the usual explanations—clots, narrowing, or blocked vessels—do not seem to apply. A new exploratory study, published in Frontiers in Bioengineering and Biotechnology, set out to investigate this phenomenon using a sophisticated engineering tool called computational fluid dynamics, or CFD, built from repeated CT scans of the same patients over time. The researchers wanted to understand not just whether blood was reaching the kidney, but how the complex swirling patterns of blood flow around the renal arteries might be influencing the kidney’s long-term health. Their findings suggest that, very soon after surgery, subtle differences in the behavior of false-lumen flow near the renal arteries can predict which kidneys are likely to wither and which will maintain their size, even when standard imaging appears reassuring.
To appreciate the significance of this work, it helps to understand what happens during an aortic dissection. The aorta has three layers, and when a tear occurs in the innermost layer, blood can surge between the layers, peeling them apart and creating a false channel alongside the normal true channel. The true lumen and false lumen are not completely separate; they communicate through tears in the tissue, known as intimal tears or re-entry communications. These tears allow blood to move between the two channels, and the exact pattern of that movement can determine how much blood reaches vital branches, including the renal arteries. In some patients, the false lumen continues to supply one kidney after the surgical repair, and whether that kidney thrives or atrophies may depend on the subtle hemodynamics of these communications. In this study, researchers focused on six index kidneys from six men: three whose kidneys lost at least 30 percent of their volume—clear atrophy—and three age-matched comparison patients whose kidneys remained stable in size. All six kidneys were supplied by the false lumen before surgery, meaning their blood supply came from this abnormal channel rather than the true lumen. The team built detailed CFD models from CT angiography scans taken at three time points: before the operation, in the early postoperative period (3 to 37 days after surgery), and at a later follow-up. Critically, they kept the boundary conditions—the pressures and flow rates at the inlet and outlet of the model—identical across time points within each patient. This allowed them to attribute any changes in flow patterns solely to the evolving three-dimensional geometry of the aorta and its tears, not to differences in how the models were constructed. In total, they characterized 90 true-lumen/false-lumen communications, measuring their distance from the renal-ostial plane (the opening where the renal artery meets the aorta), their direction, the pressure difference across them, and the amount of trans-tear flow. They also directly computed blood flow in both renal arteries from the models and measured kidney volume using three-dimensional CT segmentation.
The results were striking, not because they were dramatic in a clinical sense, but because they were so consistent. In the atrophy group, kidney volume changes were stark: one kidney lost 53.0 percent of its reference volume, another lost 64.1 percent, and a third lost 50.6 percent. In the comparison group, the changes were far milder—minus 13.8 percent, plus 0.8 percent, and minus 10.7 percent, respectively. Yet before the surgery, no hemodynamic measure separated the two groups. This is an important point: at baseline, the kidneys that would later atrophy looked hemodynamically similar to those that would remain healthy. The discriminating features only emerged after the operation altered the dissection’s flow dynamics. From the early postoperative model onward, two aortic-level flow measures distinguished every atrophying kidney from every comparator. The first was the false-lumen flow-magnitude fraction at the renal-ostial plane—essentially, how much of the blood flowing past the renal artery opening was moving within the false lumen versus the true lumen. In the atrophy group, this fraction ranged from 0.03 to 0.10, meaning only 3 to 10 percent of the flow energy at that level came from the false lumen. In the comparators, the fraction ranged from 0.13 to 0.79, meaning the false lumen contributed much more prominently. The second measure was total peak-systolic trans-communication flow—the amount of blood shuttling back and forth through the tears between the true and false lumens at the height of each heartbeat. Here again, the separation was complete: the atrophy group had values ranging from 37.8 to 45.1 milliliters per second, while the comparators had values from 61.8 to 185.3 milliliters per second. In plain terms, kidneys that later shrank were surrounded by less false-lumen flow activity near their renal arteries soon after the repair, even though the renal artery itself appeared open on imaging.
Two additional measures separated the groups later in the timeline, offering clues about the sequence of events leading to atrophy. Index renal-artery flow—the amount of blood actually entering the affected kidney through its main artery—was similar between groups in the early postoperative period, but by the late follow-up it had fallen dramatically in the atrophy group, declining by 29.4 percent, 32.6 percent, and 63.9 percent from baseline. In the comparators, by contrast, renal-artery flow changed by only +5.9 percent, −7.4 percent, and −3.0 percent, remaining essentially stable. This suggests that the reduced false-lumen flow near the renal arteries was not merely a marker of already-established kidney damage; it appeared before the modeled decrease in renal-artery flow and, in two of the three atrophy kidneys, before substantial volume loss. The other late-separating measure was tear-exchange flow directed toward the renal-ostial level—the amount of blood moving through the tears in a direction that would bring it toward the opening of the renal artery. In the atrophy group, this flow was only 1.9 to 19.1 milliliters per second, whereas in the comparators it was 38.7 to 130.9 milliliters per second. Notably, the false-lumen-to-true-lumen pressure ratio did not separate the groups at any time point. This is a crucial finding because it challenges the common assumption that pressure is the key driver of branch-vessel perfusion. The researchers could not detect a difference in pressure between the two groups, yet the flow-based measures told a completely different story. This highlights the value of computational fluid dynamics: it captures complex, three-dimensional, time-varying flow phenomena that simple pressure measurements or standard imaging cannot reveal.
To probe the underlying mechanics further, the team conducted a computational experiment in one patient-derived geometry. They took a model of an actual patient’s aorta and sequentially closed idealized versions of the communications between the true and false lumens. This was not a real surgical intervention, but a virtual experiment designed to explore how altering the tear geometry might affect flow distribution. The results were illuminating and somewhat cautionary: closing one tear did not simply reduce flow through that tear; it redistributed and even reversed flow through the remaining communications. After the final closure, the index renal-artery flow was similar to baseline, suggesting that the overall effect of multiple closures could be neutral or even beneficial, but also that the intermediate steps are highly unpredictable. In other words, if a surgeon were to intervene on a single tear in an attempt to improve renal perfusion, the flow might shift in unexpected ways, potentially worsening the situation. This is only a single simulated geometry with idealized closures, so the findings are far from definitive, but they underscore the complexity of aortic dissection hemodynamics and the dangers of oversimplified assumptions. The authors are careful to frame their conclusions as hypothesis-generating rather than proof. With only three kidneys in each group and multiple measures examined, the associations are suggestive but not causal. The study does not establish that reduced false-lumen flow causes kidney atrophy; it only shows that the two are linked in time. It also does not directly measure renal parenchymal perfusion—the actual blood flow through the microscopic vessels within the kidney tissue—so the bridge between aortic-level flow phenomena and tissue-level damage remains inferred rather than observed. Furthermore, the study does not define a treatment threshold, meaning clinicians cannot yet use these findings to decide whether a particular patient needs an additional procedure.
Despite these limitations, this study is a meaningful step forward in understanding a clinical problem that has long defied simple explanations. It demonstrates that computational fluid dynamics, when built from serial CT scans and analyzed with consistent boundary conditions, can reveal hemodynamic signatures that are invisible to the naked eye on standard imaging. The idea that a kidney could be at risk even when its renal artery looks perfectly open is both troubling and intriguing; this research suggests that the answer may lie not in the artery itself, but in the dynamic flow environment around it, in the pulsatile ebb and flow of blood through the false lumen and the tears that connect it to the true lumen. For patients who undergo aortic dissection repair, the hope is that one day such modeling could be used to identify early—perhaps even before the kidney starts to shrink—which patients are at risk for renal atrophy and might benefit from closer monitoring or earlier intervention. For researchers, the study opens new questions: Why does the false-lumen flow fraction matter so much? Is it the direction of flow, the timing, or the sheer magnitude that influences renal health? Could a surgical technique be modified to preserve a certain level of false-lumen flow near branch vessels? And can virtual experiments like the tear-closure simulation be refined and validated to guide future procedures? The path from computational fluid dynamics to bedside decision-making is long, but studies like this one build the bridge one careful observation at a time. It is a reminder that the body’s inner workings are more complex than our current tools can fully capture, and that sometimes the most important clues are not in the obvious places—not in the open artery, not in the pressure readings, but in the subtle, swirling currents of blood that surround our organs and quietly determine their fate. The research is published with open access, and the article reference is: Chen, B., Shao, S., Gao, S., Huang, T., Luo, Y., Qi, X., Wang, C., Zhang, K., Li, Y., & Yang, C. (2026). Serial computed tomography angiography-based computational fluid dynamics characterizes reduced near-renal tear exchange in kidneys that develop atrophy after aortic dissection repair. Frontiers in Bioengineering and Biotechnology, 14, Article 1945232. https://doi.org/10.3389/fbioe.2026.1945232. As with any exploratory study, these findings must be confirmed in larger, more diverse patient populations, but they offer a tantalizing glimpse of a future where personalized computational models might help protect the kidneys—and other organs—from the hidden consequences of aortic dissection repair.