

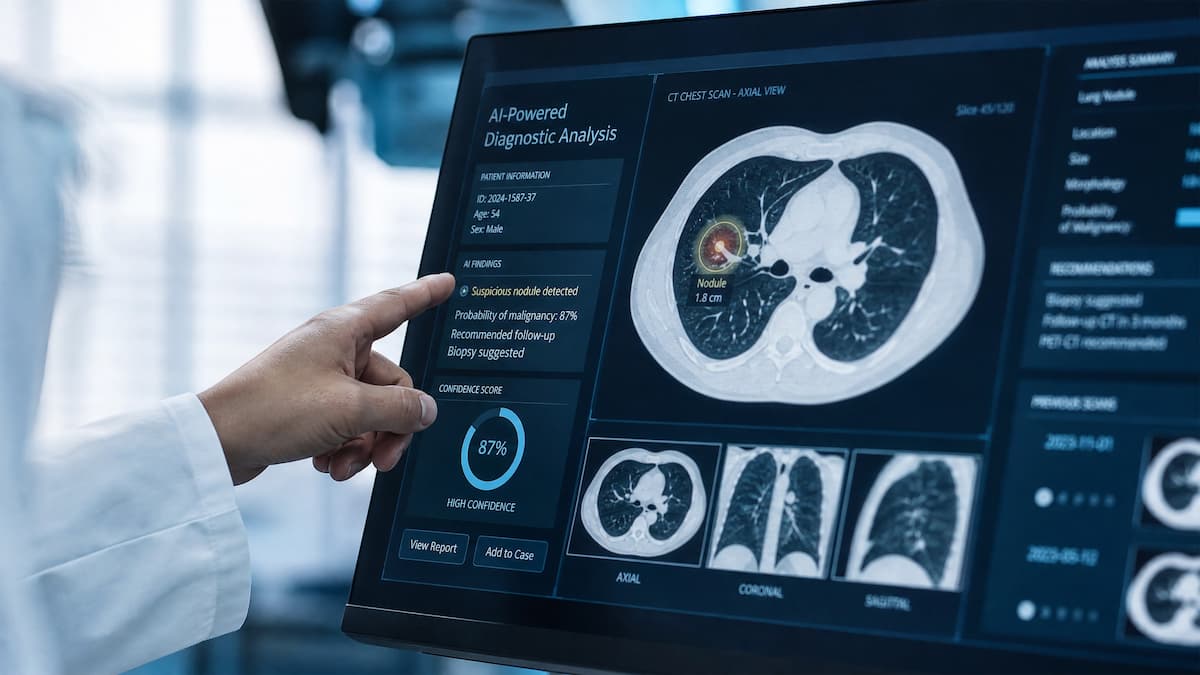
Lung cancer screening with low-dose CT is one of the most powerful tools we have for catching the disease early, when treatment can be most effective. But for the people who go through it, screening is not just a test—it is an experience filled with hope, anxiety, and uncertainty. A scan can reveal shadows, spots, or nodules that may turn out to be nothing at all, and yet the period between that finding and the final answer can feel like an eternity. Understanding this emotional reality is essential, because screening is not a single event but a lifelong process. Two recent studies offer important insights into how patients experience lung cancer screening, particularly when the results are not clean or normal. The first study, led by Louise M. Henderson, Ph.D., is a qualitative investigation built on in-depth interviews with patients who received false positives. The second, led by Hsiao and colleagues, is a quantitative retrospective cohort analysis examining how false positives affect whether patients return for future screening. Together, these studies reveal a profound tension: false alarms can frighten people, but they do not necessarily drive them away from screening. In fact, for some patients, a scary result makes them more determined to stay vigilant. At the same time, however, patients consistently ask for more honesty, more explanation, and more human connection from the clinicians who guide them through these uncertain moments.
Henderson and her colleagues sat down with fifty patients who had experienced false positives during lung cancer screening, and their conversations exposed a striking communication gap. Over and over again, patients said there were topics they wished their clinicians had discussed with them before they ever stepped into the scanner. They wanted a clearer explanation of what the lung cancer screening process really involved, from the initial appointment through follow-up scans. They wanted to understand their personal risk for lung cancer and what the screening might cost them in both money and time. They wanted to know what it meant to have nodules in their lungs, because the word “nodule” can seem benign or terrifying depending on how it is presented. They wanted to understand the additional testing that often follows an abnormal finding, including its risks, costs, and potential complications. Most importantly, they wished someone had told them that false positives were possible. As one patient put it, “Just being told you could have a false alarm would be nice. I don’t remember anyone ever saying you could get a false alarm.” Another patient recalled, “[Clinicians] really didn’t say there was any risk to screening.” These are not abstract complaints; they are calls for dignity and transparency. The patients did not want to be shielded from difficult information. They wanted to be trusted with the truth so they could prepare themselves emotionally and practically. The study also revealed that patients prefer verbal communication, especially when results are positive, rather than impersonal messages delivered through patient portals or mailed letters. A phone call, a human voice, a moment of shared understanding—these small gestures can transform a frightening experience into one in which patients feel supported. The value of honest conversation, it seems, cannot be overstated.
The second study, conducted by Hsiao and colleagues, took a very different approach but arrived at a related conclusion. The researchers looked back at the records of patients who had low-dose CT scans at a multisite lung cancer screening program in Seattle broadly, using a standardized system called Lung-RADS to categorize results. Lung-RADS, which stands for Lung CT Screening Reporting and Data System, was developed by the American College of Radiology to give clinicians and patients a common language for discussing scan findings. It takes into account the size, shape, and characteristics of any nodules seen on the scan, and it assigns a category from 1 to 4. Categories 1 and 2 are considered negative or benign, meaning no significant findings. Categories 3, 4A, 4B, and 4X represent increasing levels of suspicion, from probably benign to highly suspicious. In this study, the researchers defined a false positive as a scan with a Lung-RADS category of 3, 4A, 4B, or 4X that later turned out to be clinically stable or resolved within twelve months, meaning no cancer was actually present. Negative scans were those rated Lung-RADS 1 or 2. The question was whether people who experienced such false alarms would still come back for screening within the recommended window, which the researchers defined as five to fifteen months after the initial scan or after the positive finding had been resolved. This definition matters because staying in routine screening is essential for early detection. If a false positive frightens people away, it could undermine the entire purpose of a screening program.
The results of Hsiao’s study are both surprising and reassuring. After accounting for patients who had enough follow-up time to be included in the analysis, the researchers had a final group of 2,495 patients. Of those, 150 had experienced a resolved false positive finding, and 2,854 had negative findings initially, though that number was trimmed when follow-up time was factored in. Among the patients who had false positives, just over half—52 percent—returned for another screening within the expected time window. Among those with negative scans, just under half—43 percent—returned. That means people who received an initial scare were actually more likely to stay engaged with screening than people whose first scan was entirely normal. When the researchers adjusted for various patient characteristics and other covariates, the difference shrank a little, but the overall pattern remained. Perhaps more striking, the greatest difference appeared among patients whose initial scans were the most concerning. People in Lung-RADS categories 4B or 4X, meaning the scan was highly suspicious for cancer, were significantly more likely to return for follow-up screening after their false positive was resolved than people with negative scans were. In other words, the more frightening the false alarm, the more committed many patients became to continued screening. This makes sense from a psychological perspective: an intense scare can heighten awareness of vulnerability, making the possibility of lung cancer feel more real and personal. Rather than denying the risk or avoiding the scanner, these patients seemed to decide that staying on top of their health was their best defense.
What does this mean for clinicians and public health advocates? Hsiao and her colleagues suggest that “highly suspicious” false positives may lead to ongoing lung cancer concern among patients, and that this concern can actually drive future screening behavior. To put it more colloquially, a lung cancer screening false alarm that was suggestive of a serious cancer may make people more, not less, likely to get screened in the future. This is a counterintuitive finding, because we might assume that a false alarm would make people distrust the screening process or feel that it was not worth the emotional toll. Yet the data shows that many patients reacted differently. They did not say, “Why bother?” Instead, they seemed to say, “I need to watch this closely.” The experience of being told something looked suspicious, then being told it was fine, left an emotional imprint that made the threat of lung cancer seem real. It also made the value of screening feel more immediate. At the same time, the difference between the two groups was not enormous, and a substantial portion of patients who had negative scans did not return for screening at all. That is a separate concern, because people with normal scans may feel a false sense of security and skip future screenings. The researchers’ findings remind us that patient behavior after screening is shaped by emotion, memory, and personal reasoning. We cannot treat a normal result as the end of the story, nor can we assume that a scary result will always motivate vigilance. Each patient processes medical information differently, and the system needs to support all of them.
Perhaps the most human moment in Henderson’s study comes from a patient who expressed an accepting, almost philosophical attitude toward false positives. “I’d still want to know,” the patient said. “I’d probably be upset about a bad call, but what are you gonna do? I would still do it again.” There is something deeply admirable in that response. It acknowledges the discomfort of uncertainty, the frustration of being told you might have cancer when you do not, and the fear that comes with being tested. Yet it also reflects a mature understanding that screening is ultimately about reducing risk, not avoiding distress. This quote captures why clear communication matters so much. Patients are resilient. They can manage bad news, confusing results, and even mistakes—but they cannot manage silence. They cannot manage being left in the dark, wondering what a nodule means, what a false positive is, or whether they are at risk. The two studies together tell a story about the partnership between patients and clinicians. One study shows the emotional and informational needs patients have. The other shows that even after a frightening experience, patients are often willing to keep showing up. It is our responsibility, as a healthcare community, to meet them halfway. That means explaining the process before it starts, preparing them for the possibility of false positives, talking through what nodules mean in plain language, listening to their preferences, and making sure that when results are delivered, they come with compassion and context. Lung cancer screening saves lives, but it works best when patients are treated not as subjects or statistics, but as people who deserve to understand their own health.